
Common Symptoms
- Prominent, fluctuant swelling directly over the tip of the elbow (olecranon process)
- Tenderness on direct pressure over the posterior elbow, often worse when leaning on hard surfaces
- Warmth and erythema of the overlying skin in septic or inflammatory bursitis
- Pain at the extremes of elbow flexion as the distended bursa is compressed
- Preserved elbow range of motion in non-septic bursitis, with full extension usually maintained
- Fever, chills, and regional lymphadenopathy indicating septic bursitis requiring urgent drainage
Olecranon Bursitis Imaging Signs: Septic vs Non-Septic Elbow Swelling
Swollen bump on the back of the elbow? Learn the signs of septic vs non-septic olecranon bursitis, when imaging helps and which red flags need urgent care.
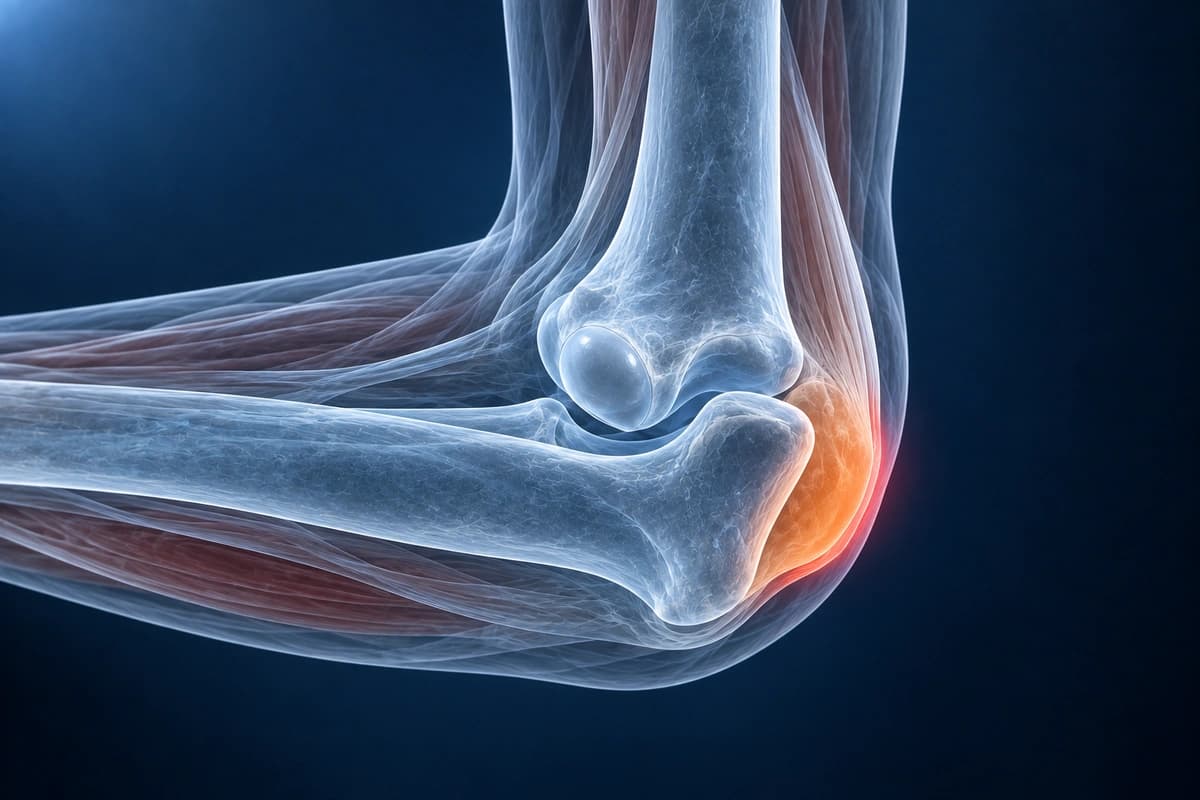
Olecranon bursitis is inflammation of the olecranon bursa, a thin fluid-filled sac located over the bony prominence at the tip of the elbow. The condition presents as posterior elbow swelling and can be caused by repetitive pressure, acute trauma, infection (septic bursitis), or inflammatory conditions such as gout or rheumatoid arthritis. Ultrasound can confirm a superficial compressible bursal fluid collection, X-ray can check for olecranon fracture, spur, or calcification, and MRI is valuable when infection, deeper soft tissue spread, or associated tendon and bone pathology must be assessed. Our AI consortium evaluates elbow imaging to characterize bursal fluid collections, wall thickening, and surrounding tissue changes.
Because a swollen posterior elbow may be traumatic, inflammatory, crystal-related, or infected, imaging should be paired with clinical red flags. Warmth, spreading redness, fever, puncture wound, or rapidly recurrent fluid should prompt clinician review for aspiration. For broader elbow injury context, compare elbow fracture and radial head fracture.
What We Look For on Imaging
- Fluid collection within the olecranon bursa with signal characteristics
- Ultrasound-visible superficial bursal fluid that may be simple or complex
- Bursal wall thickening and enhancement suggesting inflammation or infection
- Surrounding soft tissue edema extending beyond the bursa
- Complex fluid or internal debris indicating septic or hemorrhagic bursitis
- X-ray-visible olecranon bony changes including spurs, erosions, or fracture
- Rice bodies or synovial proliferation in chronic inflammatory bursitis
Frequently Asked Questions
How is septic olecranon bursitis distinguished from non-septic bursitis?
Septic bursitis is caused by bacterial inoculation through adjacent skin abrasion, puncture wound, or hematogenous spread, most commonly by Staphylococcus aureus. Clinical features favoring septic bursitis include surrounding cellulitis extending beyond the bursa, skin warmth and erythema, fever, and a history of local trauma or skin break. Bursal fluid aspiration and analysis is the definitive diagnostic step: white cell count exceeding 50,000 cells/mm³ with predominant neutrophils, positive Gram stain, or positive culture confirms infection. Non-septic bursitis may follow repetitive friction (student's or miner's elbow), gout, or rheumatoid disease, and fluid is typically less cloudy with lower cell counts and positive crystal analysis in crystal arthropathy.
What is the role of aspiration in olecranon bursitis management?
Aspiration serves both diagnostic and therapeutic purposes. Removing bursal fluid immediately reduces pain and swelling and allows the bursa wall to appose, potentially expediting resolution. Fluid should be sent for culture, sensitivity, Gram stain, cell count and differential, and crystal analysis to guide management. For septic bursitis, aspiration is combined with systemic antibiotics; repeated aspiration or surgical incision and drainage is required if fluid re-accumulates rapidly or the patient fails antibiotic therapy. For non-septic bursitis, aspiration may be combined with corticosteroid injection to reduce recurrence, though injection carries a small risk of skin atrophy, hypopigmentation, and secondary infection if the bursa is inadvertently misclassified.
Is ultrasound, X-ray, or MRI better for olecranon bursitis?
Ultrasound is often useful for confirming that the swelling is fluid within the superficial olecranon bursa and for guiding aspiration when a clinician needs fluid analysis. X-ray does not diagnose bursitis directly, but it helps look for an olecranon spur, calcification, fracture, or foreign body after trauma. MRI gives the broadest soft tissue view when infection, abscess, osteomyelitis, triceps tendon involvement, or another cause of posterior elbow swelling is a concern.
When is surgical bursectomy needed for olecranon bursitis?
Surgical excision of the olecranon bursa is reserved for chronically recurrent non-septic bursitis that fails repeated aspiration and conservative measures, or for septic bursitis that does not resolve with antibiotics and percutaneous drainage. Open bursectomy involves complete excision of the bursal sac through a posterior elbow incision, with care taken to avoid violating the triceps tendon. The posterior elbow incision is prone to wound healing complications due to poor skin vascularity and constant motion, and patients should be counseled on a significant wound complication rate compared to operations on other anatomical sites. Endoscopic bursectomy has emerged as an alternative with potentially lower wound complication rates but requires specialized instrumentation.
Sources
- Blackwell JR, Hay BA, Bolt AM, Hay SM. Olecranon bursitis: a systematic overview. Shoulder Elbow. 2014;6(3):182-190.
- Baumbach SF, Lobo CM, Badyine I, et al. Prepatellar and olecranon bursitis: literature review and development of a treatment algorithm. Arch Orthop Trauma Surg. 2014;134(3):359-370.
- Sayegh ET, Strauch RJ. Treatment of olecranon bursitis: a systematic review. Arch Orthop Trauma Surg. 2014;134(11):1517-1536.
- American Academy of Orthopaedic Surgeons. Elbow (Olecranon) Bursitis. OrthoInfo.
Get an educational explanation of imaging terms related to Olecranon Bursitis
Upload your MRI or X-ray DICOM files for private, AI-powered analysis. 4 models analyze independently — raw scan files stay in your browser.
Upload & AnalyzeMedical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer