
Common Symptoms
- Pain and burning on the outer side of the elbow that worsens with gripping or lifting
- Weak grip strength, making it difficult to hold cups, tools, or rackets
- Tenderness directly over the lateral epicondyle, the bony prominence on the outer elbow
- Pain that radiates down the forearm toward the wrist during resisted wrist extension
- Morning stiffness around the elbow that eases with gentle movement
- Increased pain when shaking hands or turning a doorknob
Lateral Epicondylitis MRI Signs: Tennis Elbow Tendon Tear Grading
Your MRI shows lateral epicondylitis or a common extensor tendon tear? Learn what tennis elbow findings mean, how tears are graded and when ultrasound helps.
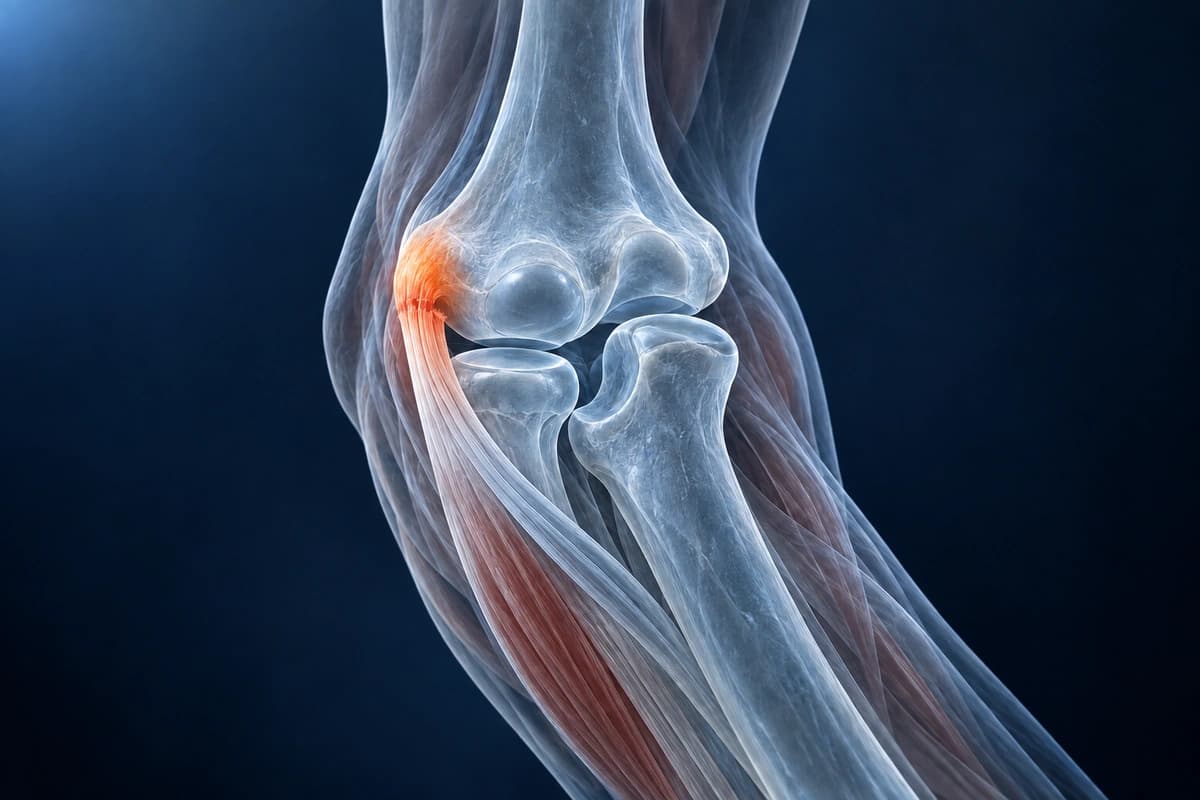
What Your MRI Report Means by Common Extensor Tendinosis or Tear
“Common extensor tendinosis” means the shared tendon that anchors the wrist and finger extensors to the outer elbow has degenerated and thickened, the MRI picture of tennis elbow. A “tear” on top of that means some fibers have pulled apart. Reports grade it from tendinosis through partial-thickness tear to a full-thickness tear with retraction.
Upload Elbow ImagingPhrases radiologists use for the extensor origin
- “Common extensor tendinosis” or “tendinopathy at the lateral epicondyle”
- “Interstitial tear” or “intrasubstance tear” of the common extensor tendon
- “Partial-thickness tear involving less than 50%” or “more than 50% of the tendon thickness”
- “High-grade partial tear” of the common extensor origin
- “Full-thickness tear with retraction” of the extensor origin from the epicondyle
- “Thickening of the lateral ulnar collateral ligament”, often reported alongside
From tendinosis to a full-thickness tear
Tendinosis is the mildest finding: the tendon is thickened and brighter than normal on fluid-sensitive images, but its fibers still attach. Surgical and tissue studies show degeneration with disrupted collagen and new small vessels rather than inflammation, which is why radiologists prefer tendinosis to epicondylitis.
An interstitial or intrasubstance tear is a split inside the tendon that does not reach its surface. A partial-thickness tear reaches a surface, and the percentage is the radiologist's estimate of how much of the tendon thickness is torn; “high-grade” means most of it. A full-thickness tear crosses the whole tendon, and “retraction” means the torn end has pulled back from the bone, usually measured in millimetres.
A higher grade does not reliably mean more pain. In one study, radiologists agreed well on the MRI grade, yet the severity of the signal change did not track symptoms. Severe tendon changes were, however, often accompanied by thickening or tears of the lateral ulnar collateral ligament, so check whether your report mentions that ligament.
When the grade matters for treatment
Most people with tennis elbow improve with time and non-operative care, whatever the MRI shows. Imaging matters more when symptoms persist and surgery is being considered: the degree of degeneration and tear on MRI corresponds well with what surgeons find, so the report helps plan the approach and rule out other causes of outer elbow pain.
Questions to bring to your appointment
- Is the tear partial or full-thickness, and roughly what share of the tendon is involved?
- Is the lateral ulnar collateral ligament normal, or does it look thickened or torn?
- Does the MRI grade change my treatment plan, or would you start the same care either way?
- If symptoms continue, at what point would injections or surgery come into the discussion?
Overview
Lateral epicondylitis (tennis elbow) is the most common cause of lateral elbow pain, involving degeneration and tearing of the common extensor tendon origin at the lateral epicondyle. Despite its name, it affects many people beyond tennis players. Our AI consortium evaluates the extensor carpi radialis brevis tendon and surrounding structures on coronal and axial MRI sequences.
The imaging goal is to grade common extensor tendinosis, identify partial-thickness tearing, and make sure lateral collateral ligament injury or radial tunnel symptoms are not being mistaken for routine tennis elbow. For modality selection, compare MRI vs ultrasound for elbow pain, and for treatment expectations see whether tennis elbow heals without surgery.
X-ray is usually normal in uncomplicated lateral epicondylitis but can help screen for arthritis, calcification, loose bodies, or fracture when symptoms follow trauma. Ultrasound can show common extensor tendon thickening, hypoechoic tearing, and Doppler hyperemia during a focused dynamic exam, while MRI gives a wider view of tendon tearing, ligament involvement, marrow edema, and nearby joint pathology. If pain started after a fall or direct blow, review elbow fracture and radial head fracture as important alternatives.
Key Imaging Findings
- Increased signal within the common extensor tendon origin on T2
- Ultrasound hypoechoic thickening or partial tearing at the extensor origin
- Partial or complete tendon tearing
- Tendon thickening and degeneration
- Lateral collateral ligament complex involvement
- Bone marrow edema at the lateral epicondyle
- Adjacent soft tissue edema
Frequently Asked Questions
Where exactly does the pain originate in tennis elbow?
The pain originates at the common extensor tendon origin on the lateral epicondyle, where the extensor carpi radialis brevis and other wrist and finger extensor tendons attach to bone. Repetitive eccentric loading causes microtears in this origin, leading to a degenerative tendinopathy rather than a purely inflammatory process. MRI typically shows increased signal within the common extensor tendon at or just distal to the lateral epicondyle.
Can X-ray or ultrasound show tennis elbow?
X-ray usually cannot show the tendon degeneration itself, but it can reveal calcification near the lateral epicondyle, elbow arthritis, loose bodies, or fracture patterns that change the differential diagnosis. Ultrasound can directly evaluate the common extensor tendon for thickening, hypoechoic degeneration, small tears, and hyperemia, especially when the examiner can reproduce the painful area. MRI is more comprehensive when symptoms are persistent, atypical, traumatic, or when ligament or joint involvement needs to be excluded.
Does tennis elbow require surgery?
The vast majority of lateral epicondylitis cases resolve with non-operative treatment within 6 to 12 months. A structured physical therapy program targeting eccentric strengthening of the wrist extensors is the cornerstone of care, supplemented by activity modification, NSAIDs, and counterforce bracing. Corticosteroid injections provide short-term relief but may impair long-term tendon healing. Surgical debridement of the degenerative tendon origin is reserved for cases that fail at least 6 months of conservative management.
How is tennis elbow different from golfer's elbow?
Lateral epicondylitis involves the common extensor tendon origin on the outer (lateral) epicondyle, while medial epicondylitis (golfer's elbow) involves the common flexor–pronator tendon origin on the inner (medial) epicondyle. Tennis elbow pain is provoked by resisted wrist extension and third-finger extension, whereas golfer's elbow pain is provoked by resisted wrist flexion and forearm pronation. Both conditions are tendinopathies driven by overuse rather than acute inflammation.
Sources
- Nirschl RP, Pettrone FA. Tennis elbow. The surgical treatment of lateral epicondylitis. J Bone Joint Surg Am. 1979;61(6A):832-839.
- Kraushaar BS, Nirschl RP. Tendinosis of the elbow (tennis elbow). Clinical features and findings of histological, immunohistochemical, and electron microscopy studies. J Bone Joint Surg Am. 1999;81(2):259-278.
- Walton MJ, Mackie K, Fallon M, et al. The reliability and validity of magnetic resonance imaging in the assessment of chronic lateral epicondylitis. J Hand Surg Am. 2011;36(3):475-479.
- Potter HG, Hannafin JA, Morwessel RM, et al. Lateral epicondylitis: correlation of MR imaging, surgical, and histopathologic findings. Radiology. 1995;196(1):43-46.
- Bredella MA, Tirman PF, Fritz RC, et al. MR imaging findings of lateral ulnar collateral ligament abnormalities in patients with lateral epicondylitis. AJR Am J Roentgenol. 1999;173(5):1379-1382.
- Walz DM, Newman JS, Konin GP, Ross G. Epicondylitis: pathogenesis, imaging, and treatment. Radiographics. 2010;30(1):167-184.
- American Academy of Orthopaedic Surgeons. Tennis Elbow (Lateral Epicondylitis). OrthoInfo.
Related Articles
Learn about lateral epicondylitis natural healing rates, physical therapy options, and when surgical intervention is needed.
Understand common elbow conditions including tennis elbow, golfer's elbow, UCL tears, radial head fractures, and OCD lesions.
Compare MRI and ultrasound for tennis elbow, golfer's elbow, UCL tears, and biceps injuries — strengths, limitations, cost, and dynamic assessment.
Get an educational explanation of imaging terms related to Tennis Elbow
Upload your MRI or X-ray DICOM files for private, AI-powered analysis. 4 models analyze independently — raw scan files stay in your browser.
Upload & AnalyzeMedical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer